


By Peter A. McCullough, MD, MPH
In many ways independent media has become a savior for the public who has been divided into right and left by the mainstream media who seem to be run by the RNC and DNC, respectively. I enjoyed meeting a newcomer to this space, Jenn Godfrey, who I have the honor of being her first follower on Twitter (X).
A two-hour-plus interview that plays like a case file being read aloud: McCullough walks through his pandemic history, the institutional failure he says nobody will examine, and then spends the back half on autism, vaccine policy, and — the role of The Wellness Company.
⚡ The Short Version
Jenn Godfrey (Keeping It Real) interviews Dr. Peter McCullough — internist, cardiologist, president of the McCullough Foundation, Chief Scientific Officer of The Wellness Company. The through-line is a single accusation: the medical establishment ran a global experiment, watched it fail, and then erased the record rather than review it. McCullough frames the SARS-CoV-2 pandemic as the third act in a century-long pattern of institutional denial, alongside cocaine and tobacco, and argues the same reflex is now protecting the excessive childhood vaccine schedule.
👤 Who’s Talking
McCullough’s self-presentation: Baylor undergrad, UT Southwestern medical school, internal medicine at the University of Washington, public health training at Michigan, cardiology fellowship at William Beaumont; former chief of cardiology, chief academic/scientific officer, program director, vice chief of medicine; fourth decade of practice in Richardson, Texas.
His credential argument: one of the most-published physicians on COVID-19 and was the most-published researcher in his earlier kidney-and-cardiovascular niche. His answer to “you’re not an infectious disease specialist” is that six years of on-the-job pandemic work and contributions to the field made him one.
His motive framing: unlike public health agencies or the White House, McCullough had a higher position in the pandemic — fiduciary duty. “It was me” responsible for his patients, not Fauci, not the FDA commissioner, not Trump or Biden.

🏥 The Central Charge: Nobody Will Review the War
No lessons-learned conference. McCullough says no major academic center — Mayo, Emory, Harvard, Michigan, UW — has held a Grand Rounds or comparative review of pandemic performance: who had the lowest mortality, the least mechanical ventilation, who kept patients out of the hospital.
No comparative hospital data. You can compare cancer outcomes or cardiac outcomes across health systems tomorrow. COVID mortality comparisons don’t exist, and he says hospital CEOs and CMOs refuse to appear before legislators to discuss them.
The silence is the evidence. He reads the absence of self-examination as “collective shame” — institutions that made the most money on the top admission diagnosis for two years have no interest in discovering they were mediocre at it.
The CME vacuum: he notes major primary-care conference agendas contain nothing on vaccine complications or lessons learned.
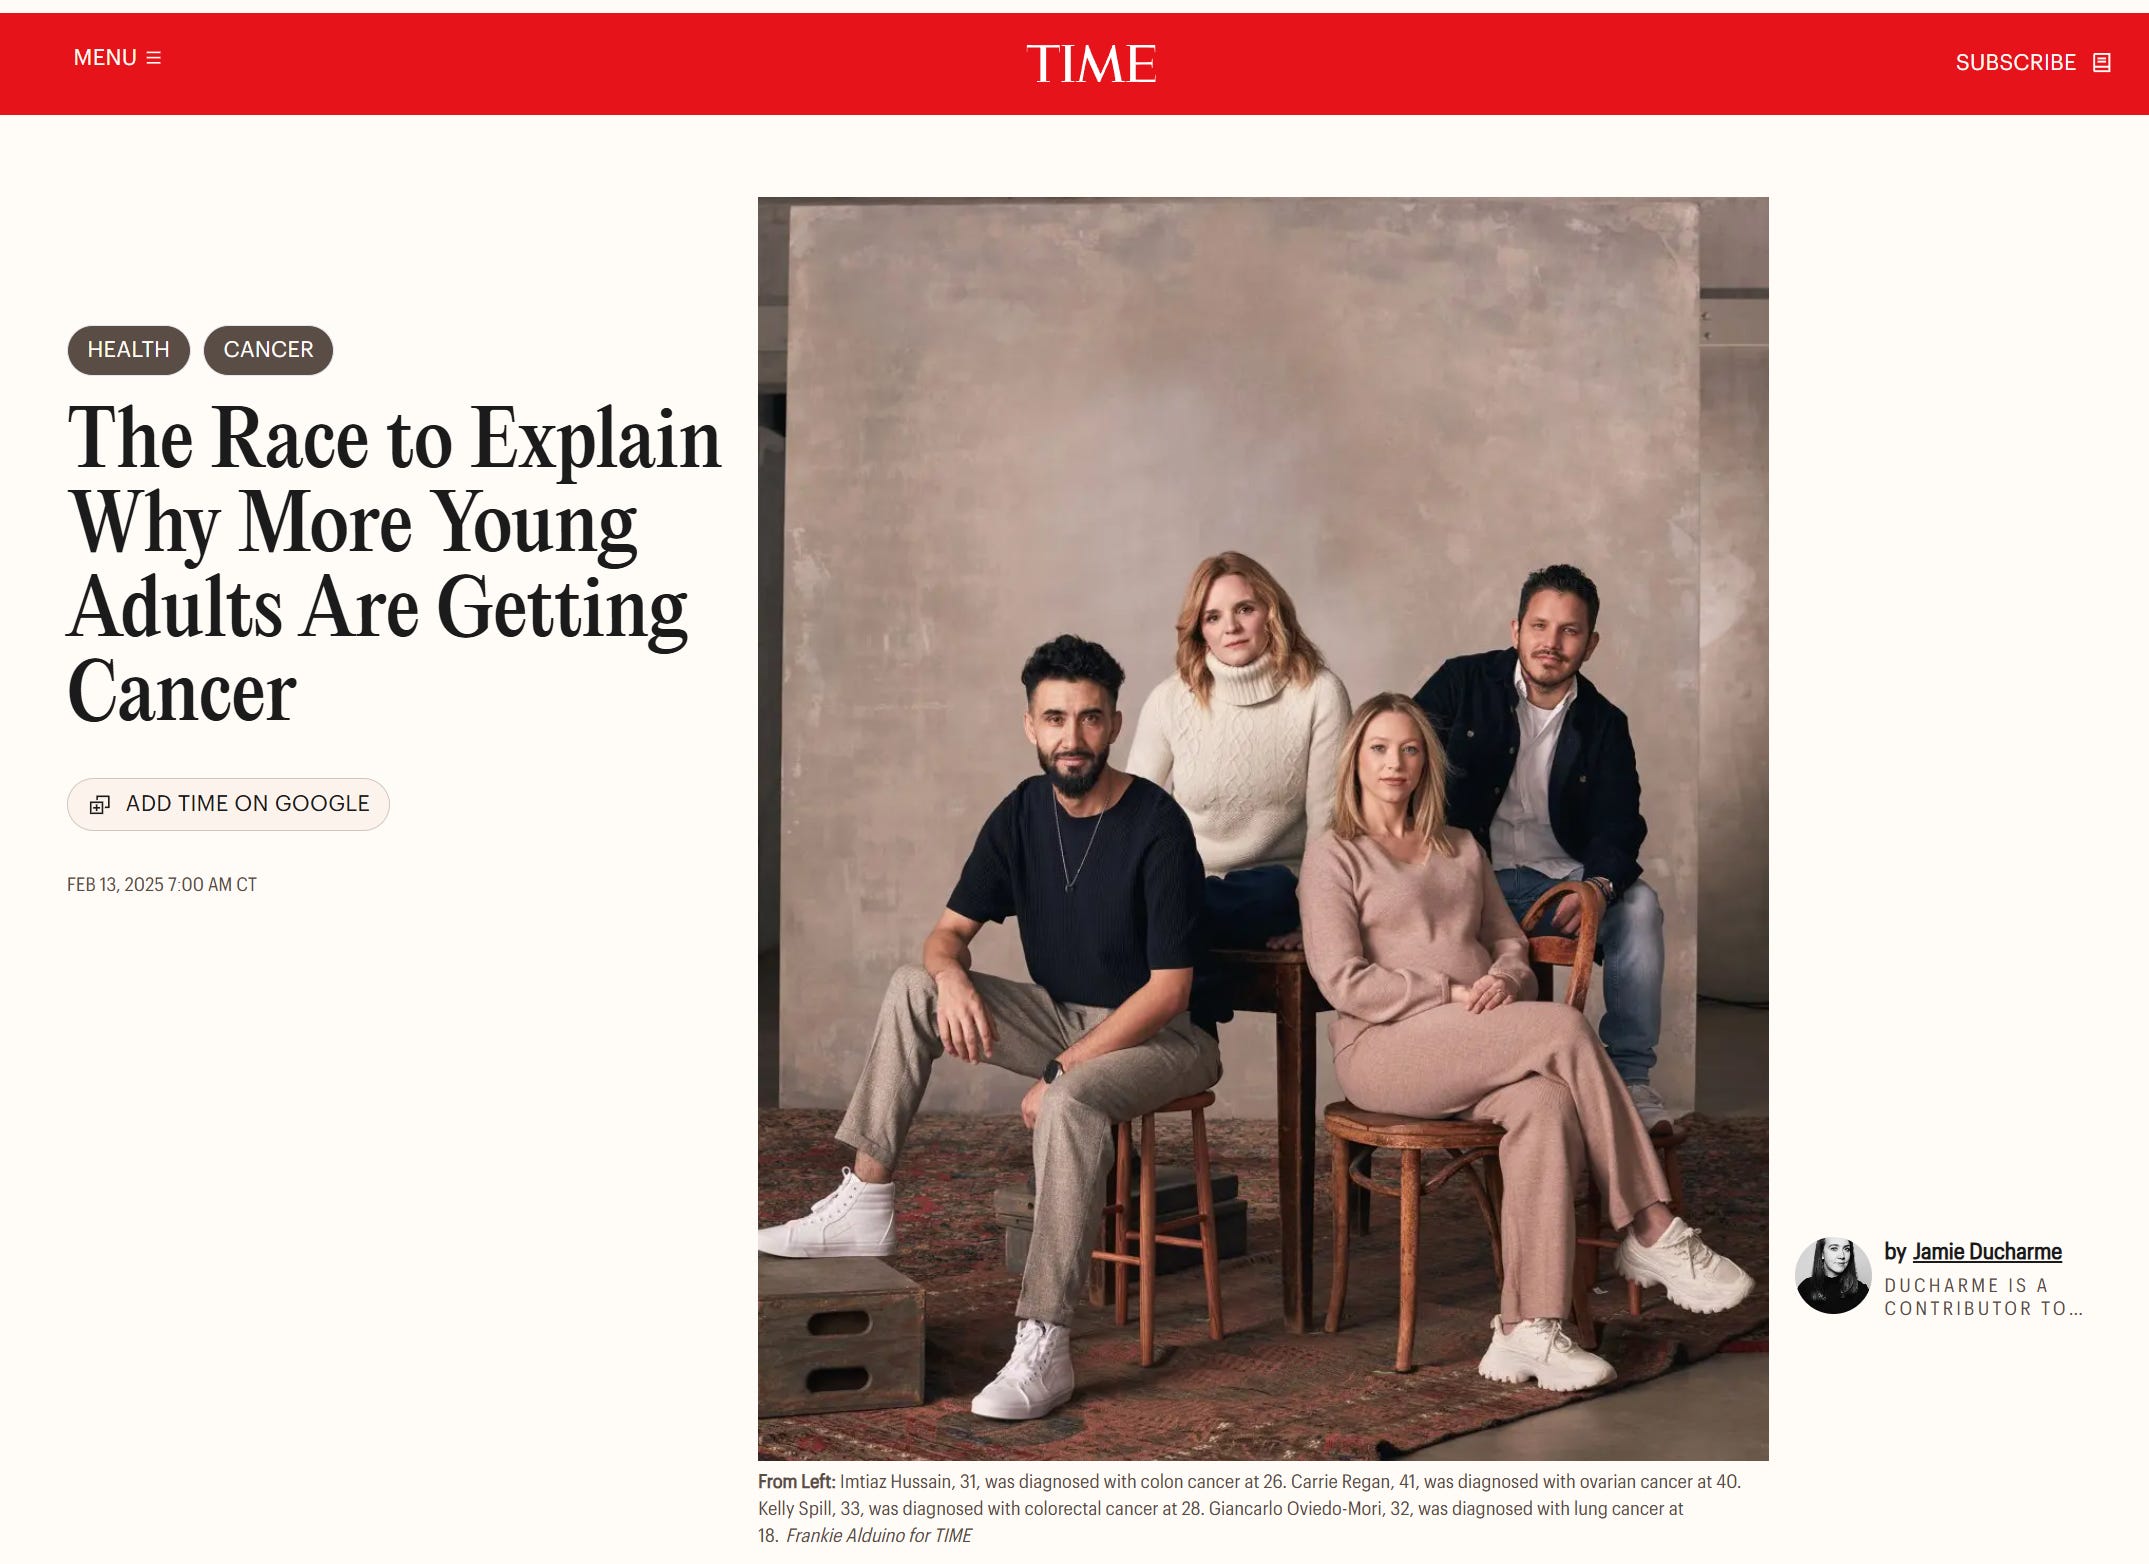
The TIME cover: he points to the 2025 TIME feature on rising cancer in young adults, where leading cancer centers floated microplastics and cell phones but — in his telling — never raised the pandemic or the vaccines as a possible inflection point.
🚬 Three Epidemics, One Pattern
His historical framework, delivered as a Chautauqua lecture:
Cocaine, 1860–1920. Nearly every major pharmaceutical product was a cocaine derivative; the literature was saturated with praise; Halsted and Freud were both addicts; only two papers in the major journals raised concern. The government had to pull it away from medicine via the Harrison Act and related laws.
Tobacco, 1920–1978. Doll and Hill’s 1950 finding was dismissed by the Medical Research Council; the British Doctors Study was smeared and Doll’s license threatened; DeBakey suspected smoking as cause of lung cancer in 1939 and was ignored; the 1964 Surgeon General’s report was rejected by the profession; the AMA didn’t publish a pamphlet on smoking harms until 1978; the tobacco settlement didn’t arrive until the 1990s.
COVID-19 pandemic, 2020–. Same architecture, faster cycle: a profession that participated en masse cannot see what it participated in.
The line that carries the whole thesis: “When everybody is self-participating (cocaine, smoking, mRNA vaccination), no one can see anything the harm.”
💊 The Treatment War
The McCullough Protocol was published in The American Journal of Medicine in 2020 — risk stratification first, then layered interventions (nutraceuticals, antivirals, antibiotics, corticosteroids, antithrombotics), roughly 25 possible interventions with 6–12 used per patient.
His contrast: the October 8, 2020 NIH ambulatory guidance amounted to do nothing — no risk stratification, no early treatment, wait for oxygen requirement, then start remdesivir.
Comparative studies: showed ~85% reductions in hospitalization and death, adoption by the Association of American Physicians and Surgeons, and uptake in Italy’s home-treatment programs. He credits the protocol with “tens of millions” of lives saved — hundreds of millions of hospitalizations avoided.
Ventilators: he argues patients were intubated too early and that his group’s permissive hypoxemia work showed patients could be managed at home on oxygen — even at saturations in the 70s — without mechanical ventilation. He notes ventilator patients were sedated, paralyzed, cut off from family, and exposed to pneumothorax and ventilator-associated pneumonia.
The payment angle: the host raises per-admission and per-ventilator reimbursement; McCullough concedes U.S. hospitals got a windfall but points out the “don’t treat” recommendation was global, so money can’t be the whole story.

💉 The Vaccine Safety Case as Presented
Fatal myocarditis, in the literature: the NEJM case of a 42-year-old man who died of autopsy-confirmed biventricular myocarditis two weeks after his second Moderna dose; the Archives of Pathology autopsy series of two teenagers found dead in bed after Pfizer; the broader autopsy review he co-authored in ESC Heart Failure.
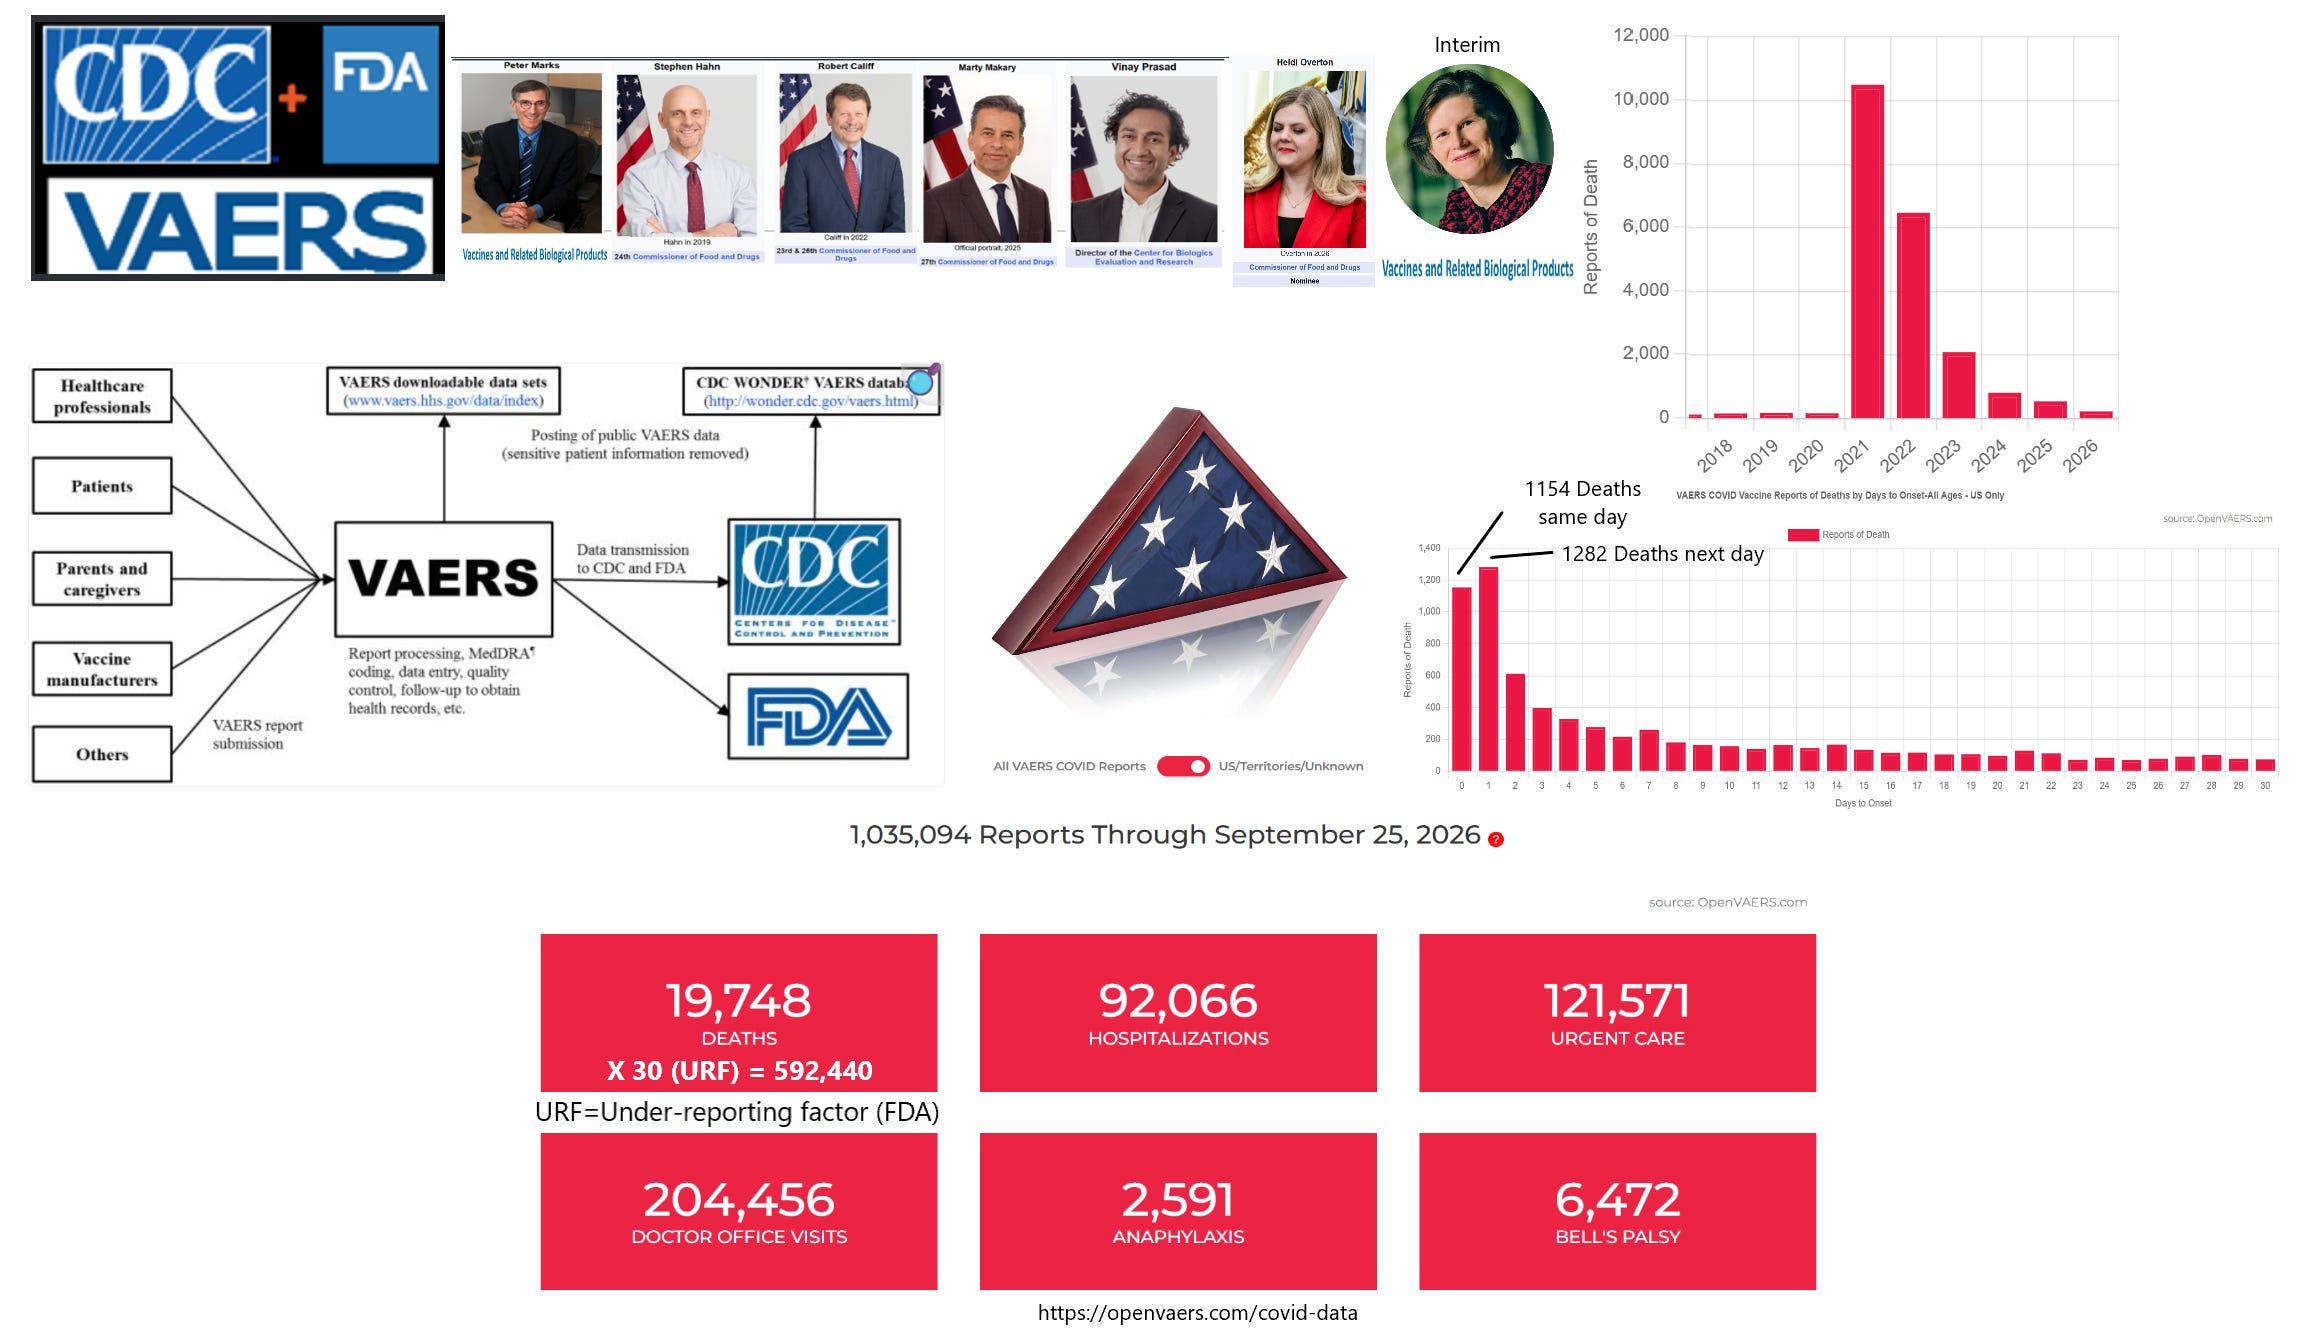
VAERS: roughly 20,000 U.S. death reports with vaccine records, lot numbers, and supporting documentation — about 1,200 on the day of the shot. He applies a 30-fold underreporting multiplier to arrive at an estimate of ~600,000 deaths, and argues many were miscoded as COVID deaths.
The “small price to pay” exchange: a neighbor told him 1,600 deaths among 60 million vaccinated was acceptable. His rebuttal: normally five to fifty deaths pull a drug off the market. Many considered the vaccine a “savior” so if some had to die with it—they were fine with someone else being collateral damage.
Mechanism: the spike protein is the toxic payload; synthetic mRNA is stabilized (pseudouridylation) so it lingers; he claims one patient had vaccine material detectable 3.5 years later; IgG4 subclass switching is offered as the explanation for delayed injury.
The injury list: myocarditis and sudden cardiac death, blood clots (he names public figures), Guillain-Barré and neurologic paralysis, autoimmune syndromes, and cancer — including the “turbo cancer” framing and his suggestion that Biden’s Gleason 9 metastatic prostate cancer fits the pattern.
Policy conclusion: pull the products. He notes Johnson & Johnson and AstraZeneca withdrew voluntarily over clots while Pfizer and Moderna did not.
🧪 The Role of The Wellness Company
“Ultimate Spike Detox” — nattokinase, bromelain, curcumin — pitched as the answer to long COVID and vaccine injury, with a LabCorp antibody test (he cites $79) and a threshold of 1,000 units/mL as the target. He says he copyrighted rather than patented it.
Emergency medical kits from The Wellness Company — pre-prescribed antibiotics, Zofran, prednisone — pitched as a hedge against ER visits and against “Operation Fortress” style 90-day disruption scenarios.


🧩 Autism: The Episode’s Emotional Core
Prevalence: CDC’s own surveillance network puts autism at 1 in 31 eight-year-olds (3.2%), ranging up to roughly 1 in 19 in California. He cites 27% profound autism — nonverbal, self-injurious, lifelong care — and a lifespan shortened by decades.
The McCullough Foundation report, Determinants of Autism Spectrum Disorder: predisposing factors (older parents, prematurity, common genetic variants, maternal immune activation, in-utero drug exposure, environmental toxicants, gut-brain dysbiosis) plus combination, early-timed vaccination as the trigger — a post-encephalitic conversion in susceptible children.
The regression narrative: children are normal at one year, receive a bundled well-baby visit of up to 16 antigens, and convert within weeks. He is emphatic that they are not born with it.
The methodological claim: of the studies finding no association, none has a valid unvaccinated control group; they rely on billing codes, never interview parents or examine children. He cites 12 studies in the report showing better overall health outcomes among completely unvaccinated children.
Policy: the CDC’s position has shifted to “the link is not ruled out”; he says the report drove that change. He recommends delaying vaccination past age four, spacing shots, and supports the push to align the U.S. schedule with Denmark’s — which he says was immediately sued by the AAP, AMA, and ACP.
The political argument: California and Texas have similar populations and identical disease rates but radically different vaccine law — so the law can’t be scientific.
The autism–gender dysphoria link: he asserts a large fraction of children with gender dysphoria are autistic, socially isolated, and suggestible — and are being steered toward irreversible interventions.
The treatment answer is sobering: he calls profound autism likely permanent brain injury, recommends microbiome and dietary strategies, and says the real fix is prevention.

🗣️ The Human Material
The host’s own stories carry the emotional weight: her Bell’s palsy after a twin delivery (used as her standing reason to decline the shot), two brothers coerced into vaccination by employers, one with persistent palpitations; an eye infection misdiagnosed as a sinus infection at urgent care that nearly became sepsis; her 14 years of sobriety and discomfort at being given fentanyl in the ER. One brother has a child with profound autism needing care at age 24. Her brother — an ER nurse at Harborview — is the source of the most damning anecdote in the episode: telling patients at triage to go home because once admitted, “you’re not leaving here.” Tragically some never did.
📝Please subscribe to FOCAL POINTS as a paying ($5 monthly) or founder member so we can continue to bring you the truth. AlterAI may be used to assist in searches, synthesis, and review.
Peter A. McCullough, MD, MPH
President, McCullough Foundation
FOCAL POINTS has partnered with AlterAI to support independent research and open inquiry. Subscribe to AlterAI today and get a discount on intellectually independent AI!

📚 References
McCullough PA, Kelly RJ, Ruocco G, Lerma E, Tumlin J, et al. “Pathophysiological Basis and Rationale for Early Outpatient Treatment of SARS-CoV-2 (COVID-19) Infection.” The American Journal of Medicine. Published online August 6, 2020. DOI: 10.1016/j.amjmed.2020.07.003.
Verma AK, Lavine KJ, Lin CY. “Myocarditis after Covid-19 mRNA Vaccination.” New England Journal of Medicine. 2021;385(14):1332–1334. DOI: 10.1056/NEJMc2109975.
Gill JR, et al. “Autopsy Histopathologic Cardiac Findings in 2 Adolescents Following the Second COVID-19 Vaccine Dose.” Archives of Pathology & Laboratory Medicine. 2022;146(8):925.
Hulscher N, Hodkinson R, Makis W, McCullough PA. “Autopsy findings in cases of fatal COVID-19 vaccine-induced myocarditis.” ESC Heart Failure. 2024. DOI: 10.1002/ehf2.14680.
Hulscher N, Leake JS, Troupe S, Rogers C, Cosgrove K. Determinants of Autism Spectrum Disorder. McCullough Foundation Report, 2025. Zenodo record 17451259; mcculloughfnd.org.
Chaufan C, Hemsing N, Moncrieffe R. “’When I had concerns about my own patients…I was told to keep quiet’: experiences of moral injury among healthcare workers under Covid-19 vaccine mandates in Alberta, Canada.” Open Medicine. 2026;21(1):20261503. (Preprint: medRxiv 2025.05.27.25328450.)
CDC. “Prevalence and Early Identification of Autism Spectrum Disorder Among Children Aged 4 and 8 Years — Autism and Developmental Disabilities Monitoring Network, 16 Sites, United States, 2022.” MMWR Surveillance Summaries. 2025;74(2).
CDC. “Autism and Vaccines.” https://www.cdc.gov/vaccine-safety/about/autism.html
Ducharme J. “The Race to Explain Why More Young Adults Are Getting Cancer.” TIME. February 13, 2025.
Leake J, McCullough PA. Vaccines: Mythology, Ideology, and Reality. Children’s Health Defense Books, 2025.
Desmet M. The Psychology of Totalitarianism. Chelsea Green Publishing, 2022.


